By Nick Hoffmeyer, Head of Marketing at Bambi · Updated October 10, 2026 · 9 min read
Rural NEMT is harder because the distances are longer, the roads are worse, there is little or no public transit to fall back on, and Medicaid only pays for the miles a rider is in the van. Most rural residents live 10 to 30 miles from the nearest hospital or pharmacy, according to the National Rural Health Association. Small operators who make it work do it by building steady trip volume from several sources and wasting as few empty miles as possible.
The data in this guide comes mainly from the NRHA policy paper Transportation barriers and solutions to care for rural older adults (July 2026), written by the National Rural Age-Friendly Initiative Interest Group, a partnership between NRHA and The John A. Hartford Foundation. It focuses on older adults, which is most of the rural NEMT rider base anyway.
What Makes Rural NEMT Different
Urban NEMT is a density problem: lots of trips, lots of traffic, tight pickup windows. Rural NEMT is a distance problem. Fewer trips, much longer ones, and a lot of road between them.
Distance and empty miles
NRHA notes that rural residents frequently live 10 to 30 or more miles from essential services, including hospitals and primary care. For an operator, that means one round trip can eat half a driver's shift. It also means the trip back to the yard, or to the next pickup, is often long and empty. Those deadhead miles are where rural margins disappear. Our guide to NEMT deadhead miles shows how to measure them and where to cut.
Roads, weather, and vehicle wear
More than 40 percent of country roads in rural areas are "inadequate for current travel" according to federal guidelines, NRHA reports, which raises safety risks and maintenance costs on vehicles. Add unpaved roads and hazardous seasonal weather and a rural van wears out faster than a city one. Budget for it, and keep a real preventive maintenance plan instead of fixing things when they break 40 miles from the shop.
Little or no public transit
Many rural counties have no public transportation at all, NRHA notes. Where transit does exist, it may run only a few days a week, during weekday business hours, with on-demand rides that need to be booked days or even weeks ahead. That makes early-morning specialty appointments and weekend trips nearly impossible without NEMT. It also means that when your company can't take a trip, there is often no backup.
Who Rural Riders Are
Rural older adults make up about a quarter of adults 65 and older in the country, according to the NRHA paper. Many are dually eligible for Medicare and Medicaid, and NRHA calls NEMT particularly critical for that group.
The trips are mostly recurring and non-negotiable. NRHA lists dialysis, chemotherapy, cardiac rehabilitation, and primary care visits as the care rural older adults depend on NEMT to reach. Standing orders like these are the backbone of a rural schedule, and dialysis in particular can mean several round trips a week for the same rider. See NEMT and dialysis for how to plan around it, and our piece on NEMT and the social determinants of health for the bigger picture.
The Money Problem: Loaded Miles, Rates, and Medicaid Pressure
Here is the uncomfortable math of rural NEMT. NRHA points out that only "loaded" mileage, when a beneficiary is in the vehicle, is reimbursed. When a rider no-shows or refuses the trip, you don't get paid for the drive out. On a 30-mile pickup, that is a lot of unpaid fuel and driver time.
NEMT is also a small line item that is easy to cut. NRHA, citing KFF, puts NEMT at less than 1 percent of total Medicaid spending, with annual federal and state expenditures around $3 billion. Meanwhile KFF estimates that the 2025 reconciliation law (Public Law 119-21) will reduce federal Medicaid spending in rural areas by $137 billion over 10 years. NRHA warns that pending Medicaid cuts make NEMT "an easy target despite its relatively small cost and outsized benefits."
What that means for a small operator: don't build a rural business on a single Medicaid broker contract and hope rates rise. Know your cost per loaded mile, track your no-show rate by route, and diversify your payers. For more on the rate side, read NEMT Rate Reality 2026, how Medicaid policy changes affect NEMT, and our revenue per vehicle deep dive.
Where Rural Trip Volume Comes From
Rural operators who last rarely depend on one source of trips. Collaboration between health care providers, local governments, transportation agencies, and community organizations is how rural trip volume actually gets built.
Brokers and county-by-county networks
Many states run Medicaid NEMT through brokers, and rural counties are often the hardest for them to cover. That is leverage. If you can reliably serve a county other providers avoid, say so. For a picture of how a broker builds rural coverage, listen to our podcast with Ray Hagan of WellTrans, a broker network that places providers county by county across all 92 Indiana counties.
Area Agencies on Aging, transit agencies, and FTA grantees
NRHA describes a web of funding streams that rarely talk to each other: Area Agencies on Aging (funded in part through Older Americans Act Title III-B), state DOTs, Medicaid, veterans' services, hospitals, and nonprofits. FTA Section 5310 funds transportation for older adults and people with disabilities, and FTA Section 5311 funds transit in rural areas under 50,000 people. Under 5311, NRHA notes, the federal share is 80 percent for capital projects and 50 percent for operating assistance, and the local match is a major barrier for small agencies.
For a private operator, the opportunity is contracting. An agency that has funding but no drivers, or a grant that only covers vehicles, may need a partner to run the trips. Call your local AAA and your rural transit agency and ask what they can't cover today.
Veterans transportation
Rural veterans rely on the VA's Highly Rural Transportation Grants, the VA Beneficiary Travel program, and volunteer networks like Disabled American Veterans. NRHA notes these programs depend heavily on aging volunteer drivers and are limited to veterans service organizations or state veterans services. The pending Rural Veterans Transportation to Care Act (H.R. 1733) would expand grant eligibility beyond highly rural areas and raise the maximum grant to $60,000. Read our guide to winning a veteran transportation grant and the wider list of NEMT grants and funding.
Hospitals, clinics, and facilities
Rural hospitals, dialysis centers, and clinics lose money when riders miss appointments, and they often have no transportation partner they trust. A direct contract with one of them can anchor a whole route. Our guide on how to get medical transportation contracts walks through the pitch.
Telehealth and Mobile Clinics: Competitor or Partner?
Telemedicine and mobile health units bring some care closer to rural residents and cut down on long trips. The American Hospital Association has written about rural health partnerships built around this digital front door. NRHA also recommends expanding mobile integrated health and community paramedicine, which reduce transportation dependence.
Don't treat that as a threat. A video visit still can't run dialysis, and a mobile unit can't do an MRI. Telehealth tends to send the riders who really need in-person care to the bigger hospital in the next county, and those are exactly the long trips an NEMT operator is built for. Partner with telehealth and mobile clinic providers so you are the first call when a rider needs to travel.
Running a Rural Fleet Day to Day
A few habits separate rural operators who make money from those who just drive a lot:
- Plan the long trips first. Book the out-of-county specialty runs, then fill the gaps around them with local trips in the same direction.
- Multi-load where your contracts allow it. Two riders heading to the same dialysis center at the same time belong in one van. See optimizing routes for group NEMT trips.
- Route on real distance. Our guide to NEMT route optimization covers the basics.
- Protect driver coverage. One sick driver can wipe out a rural day. Cross-train, keep a backup list, and read our driver recruiting and retention guide.
- Confirm the day before. On a 30-mile pickup, a reminder call that prevents one no-show pays for itself.
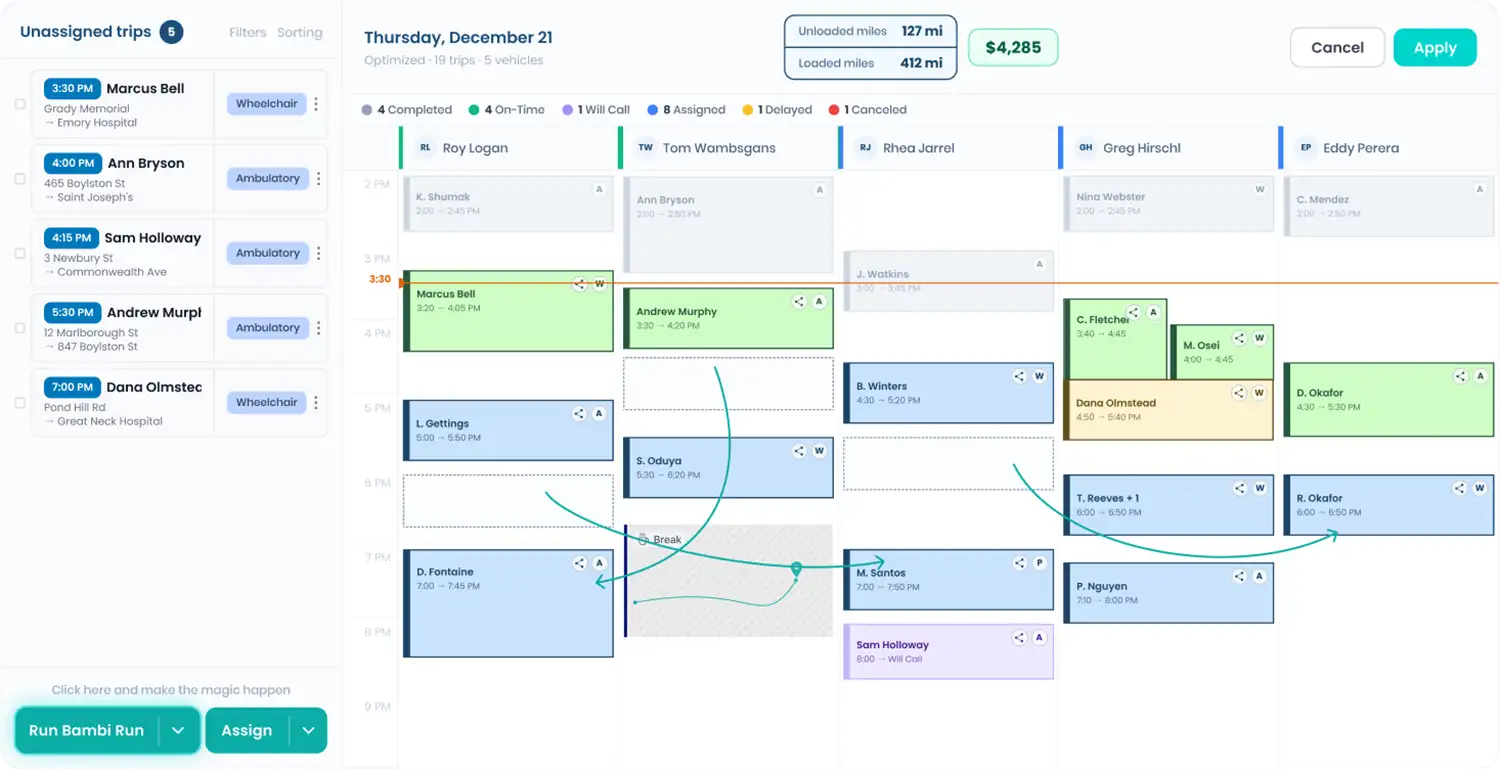
This is the work Bambi is built for. Run Bambi Run builds the day's schedule and routes, Fleet HQ shows dispatch where every vehicle is, and the Driver App gives each driver a clear manifest and a direct line to dispatch, which matters when the next pickup is half an hour away.
Rural Operators Doing It Well
- Sunshine Rides (Colorado). Based in Grand Junction, Sunshine Rides grew from a single vehicle into a Health First Colorado (Medicaid) specialist that runs long-distance trips across the state, including over the mountain passes to Denver-area hospitals. Read the Sunshine Rides spotlight.
- SVHH Transportation (Shenandoah Valley, Virginia). Started by two home health agency owners with one van to get their own clients to appointments, SVHH now serves riders across the Shenandoah Valley and beyond. Read the SVHH Transportation spotlight.
- WellTrans (Indiana). Ray Hagan explains how WellTrans places providers county by county across all 92 Indiana counties, with most of its trips in rural areas. Listen to the WellTrans episode.
What NRHA Is Asking Congress For, and What It Means for Operators
- Increase NEMT funding to reflect transportation costs, the growing number of rural older adults, and rising gas and maintenance costs. So what: if rates move, it will be because rural costs were documented. Keep good records of your cost per trip.
- Increase FTA Section 5310 and 5311 funding and adjust it for long-term operating costs like drivers, fuel, insurance, and maintenance. So what: more operating money for agencies means more contracting opportunities for private operators.
- Lower or waive FTA local match requirements in low-resource areas. So what: more small rural agencies could pursue grants, and some will need a partner to run the service.
- Increase Older Americans Act Title III-B funding with a funding floor for rural communities. So what: AAAs are a real source of private-contract trips.
- Bolster tax incentives for volunteer drivers. So what: volunteer programs that stay alive are partners for overflow, not competitors.
- Streamline VA and local transit coordination. So what: better scheduling links between VA medical centers and community transportation open the door to veteran trips.
- Reduce administrative burdens on rural agencies. So what: less paperwork for agencies can mean faster contracting with you.
FAQs
Why is NEMT harder to run in rural areas?
Trips are much longer, roads are often in poor shape, there is little or no public transit as a backup, and drivers are harder to find. Most rural residents live 10 to 30 miles from the nearest hospital or pharmacy, so each trip ties up a vehicle and driver for far longer than an urban trip does.
Does Medicaid pay for empty miles on long rural trips?
Generally no. As NRHA notes, Medicaid NEMT reimburses only loaded mileage, when the rider is in the vehicle. The drive out to a pickup and any trip where the rider no-shows or refuses are typically unpaid, which is why confirmations and tight routing matter so much in rural areas.
How do small rural NEMT companies find steady trip volume?
By combining sources: broker trips in counties other providers avoid, contracts with Area Agencies on Aging and rural transit agencies, veteran transportation programs, and direct agreements with hospitals, dialysis centers, and clinics. Recurring trips like dialysis form the base of the schedule.
Built for the Long Roads
Rural NEMT will never be easy, but it doesn't have to be chaotic. Bambi helps small fleets plan long trips, cut empty miles, and keep drivers connected to dispatch, for $69 per active vehicle per month, month to month, with no onboarding or setup fees. See pricing.
Nick Hoffmeyer is Head of Marketing at Bambi, the AI-powered dispatch and scheduling platform for non-emergency medical transportation (NEMT) providers. He works with NEMT owner-operators every day on growth, SEO, and the operational systems that help fleets run more trips with less stress. More from Nick: LinkedIn